
The Eating Disorder Spectrum
Why a spectrum, not a checklist
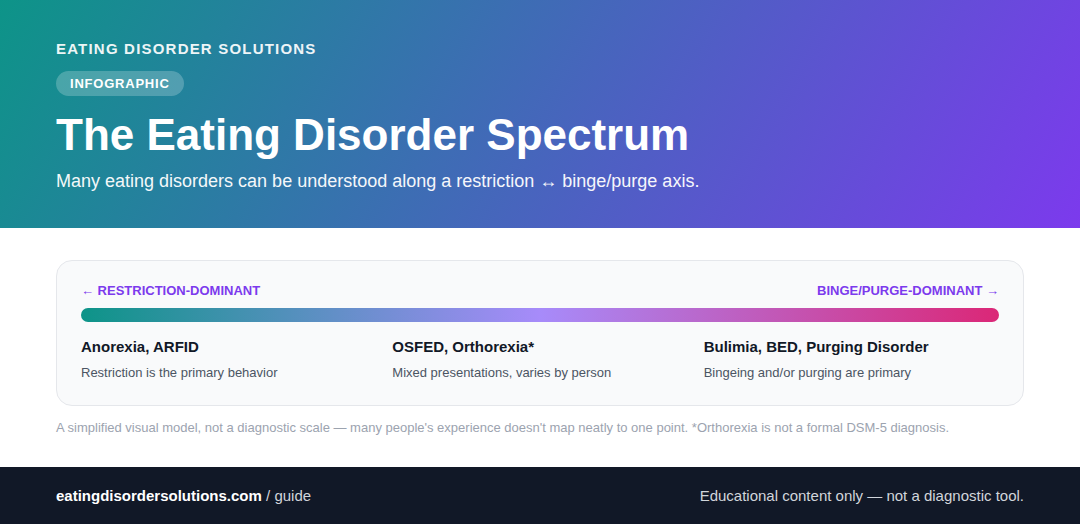
Clinical categories are useful for diagnosis and treatment planning, but they can make eating disorders look more separate from each other than they actually are in practice. A spectrum model — restriction-dominant behaviors on one end, binge/purge-dominant behaviors on the other, with mixed presentations in between — is a way of showing how these conditions relate to each other, rather than treating each diagnosis as a completely isolated box.
What “restriction-dominant” looks like
On this end of the spectrum, the primary behavior is limiting food intake — anorexia is the clearest example, and ARFID sits here too, though its underlying drivers (sensory issues, fear of choking, low interest in food) are different from anorexia’s body-image-driven restriction. What both share is that restriction is the central, defining behavior.
What “binge/purge-dominant” looks like
On the other end, the central behaviors are episodes of eating a large amount of food, often followed by compensatory behavior. Bulimia and purging disorder sit here, along with binge eating disorder — though BED specifically doesn’t involve the regular compensatory behaviors that define bulimia and purging disorder, which is part of why even “one end of the spectrum” contains real variation.
The middle: mixed and evolving presentations
OSFED and orthorexia often sit in the middle or don’t map cleanly onto either end — OSFED by definition covers presentations that mix features or don’t fully meet another category’s criteria, and orthorexia’s restriction is driven by food “purity” rather than quantity or weight. It’s also common for a person’s position on this spectrum to shift over the course of an illness.
What this model is useful for — and what it isn’t
This spectrum is a teaching tool, not a diagnostic instrument. It’s useful for understanding how conditions relate to each other and why treatment approaches sometimes overlap across categories. It’s not useful for self-diagnosing a specific condition or estimating severity.
Why the spectrum model matters for treatment planning
A diagnosis tells a treatment team which category someone falls into; a spectrum position adds information about which direction their symptoms are trending and what’s driving them day to day. In practice, this affects real decisions — a presentation trending toward the restriction-dominant end may call for closer nutritional and medical monitoring in the early stages of treatment, while a presentation trending toward binge/purge-dominant patterns may call for a stronger early focus on interrupting the compensatory-behavior cycle. Treatment teams that think in spectrum terms tend to build more individualized plans rather than defaulting to a standard protocol based on diagnosis alone.
This is also why the same diagnosis can look very different from one person to the next in treatment. Two people both diagnosed with OSFED might sit at opposite ends of this spectrum, need different intensities of medical monitoring, and respond to different therapeutic approaches — the diagnosis alone doesn’t capture that, but a spectrum-informed assessment does.
Common misconceptions about where someone falls on the spectrum
A restriction-dominant presentation is sometimes assumed to be more “under control” and therefore less urgent than a binge/purge-dominant one, because the visible behavior looks more disciplined. That assumption is not clinically accurate — both ends of the spectrum carry serious medical risk, and severity is determined by physical and psychological impact, not by which end of the spectrum someone sits on. Similarly, sitting in the mixed middle is sometimes read as “not as bad” because it doesn’t match either textbook picture as clearly — in practice, mixed and evolving presentations can be some of the more clinically complex to treat, precisely because they don’t follow one predictable pattern.
How this shows up in a first evaluation
A clinician using a spectrum-informed approach in an initial evaluation is typically listening for more than just symptom checklist items — they’re trying to build a picture of direction and dominant pattern. That usually means asking not just “what are you doing” but “how has this changed over the last several months,” “which behaviors happen most often,” and “what tends to come before and after an episode, if there is one.” Two people who’d both technically qualify for the same diagnosis can walk out of that same evaluation with meaningfully different initial treatment recommendations, because the spectrum picture — not just the diagnostic label — shapes where a team starts. If you’re preparing for a first appointment, being ready to describe patterns and changes over time, not just current symptoms, tends to make that conversation more useful for both sides.
Frequently asked questions
Does position on the spectrum indicate how severe a condition is?
No. This is a behavioral model, not a severity scale. A restrictive pattern can be just as medically serious as a binge-purge pattern, and vice versa.
Can someone move along the spectrum over time?
Yes, this is a well-documented pattern. Someone might start with primarily restrictive behavior and develop binge-purge episodes later, or move the other direction.
Where do BED and OSFED fit if they don’t cleanly match either end?
BED sits toward the binge/purge-dominant end since bingeing is its core behavior. OSFED covers presentations that mix features from multiple categories, so it doesn’t map to one fixed point.
How is this different from an official diagnostic tool?
This spectrum is an educational model to illustrate how conditions relate to each other. Formal diagnosis uses specific clinical criteria assessed by a qualified professional.
Can a treatment team use the spectrum model instead of a formal diagnosis?
Diagnosis is still typically required for insurance, medical records, and standardized treatment planning. The spectrum model is used alongside a diagnosis, as an additional layer of clinical detail, not as a replacement for one.
Does everyone with an eating disorder fit somewhere on this spectrum?
The restriction-dominant to binge/purge-dominant spectrum is most directly useful for anorexia, bulimia, BED, and OSFED presentations. Conditions like ARFID, which center on food avoidance driven by sensory issues or fear rather than a drive to control weight or shape, are typically understood through a different clinical framework — see our ARFID overview for more.
What this covers
- Frames eating disorders along a restriction ↔ binge/purge axis, a common simplified clinical model.
- Types cluster loosely rather than sitting in hard categories — overlap is normal and expected.
- This framing is a simplified model, not a full DSM-5 classification — see the full guide for diagnostic detail.